

Should you squat or sit? Many people see this choice as pure habit. Yet in clinical gut medicine, your toilet posture shapes how smoothly you pass stools. How you sit or squat shifts your pelvic floor muscles. It changes joint strain on your knees and hips. It also changes how much you strain to empty your bowels.
There is also a simple health clue many people miss. Traditional Indian toilets let you see your stool and urine before flushing. Looking at bodily waste gives helpful clues about hydration, liver function, and gut inflammation (internal tissue irritation and swelling). So which toilet is truly best for your health? The answer depends on your body, your joints, and your age.
Which Toilet Posture Is Truly Better for Your Digestive Health?
🩺 Quick Clinical Verdict: Squatting vs Sitting
Indian squat toilets shift your hips to a 35-degree angle. This posture relaxes the pelvic sling muscle and cuts bowel straining. Standard sitting leaves a 90-degree kink that can worsen hard stools. Dr. Sumaiya’s clinical recommendation: place a simple 7-inch footstool under your feet at a Western commode to empty your bowels comfortably.
The Biomechanics of Elimination: Why Squatting Straightens the Rectum
To see why toilet posture matters, look at your pelvic floor. A sling-like muscle loops around your lower rectum. This is the puborectalis muscle (the sling-like pelvic floor muscle that holds your rectum closed). It holds your lower bowel shut to stop accidental leaks.
This muscle creates a sharp bend. Doctors call this the anorectal angle (the natural bend between your rectum and anal canal that controls stool release). When you stand or sit on a chair, this angle stays around 90 degrees. That sharp bend keeps stool securely inside your body.
Think of a garden hose. If you bend the hose at a sharp right angle, water stops flowing. When you sit on a Western commode, your thighs sit at 90 degrees. That sharp bend stays in place. Passing stool through a kinked canal requires hard pushing. This hard pushing is called a Valsalva maneuver.
When you squat, your hips flex to roughly 35 degrees. Your thighs press gently against your lower belly. This deep hip flexion relaxes the pelvic sling muscle completely. The bend straightens out into a clear line. Waste moves out easily with minimal pushing.
Indian Toilet vs Western Commode: A Clinical Posture Comparison
Neither toilet design is universally better for every person. Each option brings clear body benefits and joint trade-offs:
| Clinical Metric | Traditional Indian Toilet (Squatting) | Standard Western Commode (Sitting) | Western Commode + Footstool (Semi-Squat) |
|---|---|---|---|
| Anorectal Angle | Straightened line (~35° hip angle) | Acute kink (~90° hip angle) | Straightened line (~35° hip angle) |
| Pelvic Sling Muscle | Fully relaxed; open passage | Partially tight sling | Mostly relaxed sling |
| Bowel Straining | Low; assisted by gravity | Frequent; needs hard pushing | Greatly reduced pushing |
| Knee Joint Load | High knee and hip strain | Minimal joint stress | Low joint stress; thighs rest on seat |
| Elderly Fall Risk | High risk on slick tiles | Very low; stable seat | Low; feet rest flat on footstool |
| Waste Visibility | Clear view before flushing | Lost in bowl water | Easy to check before flushing |
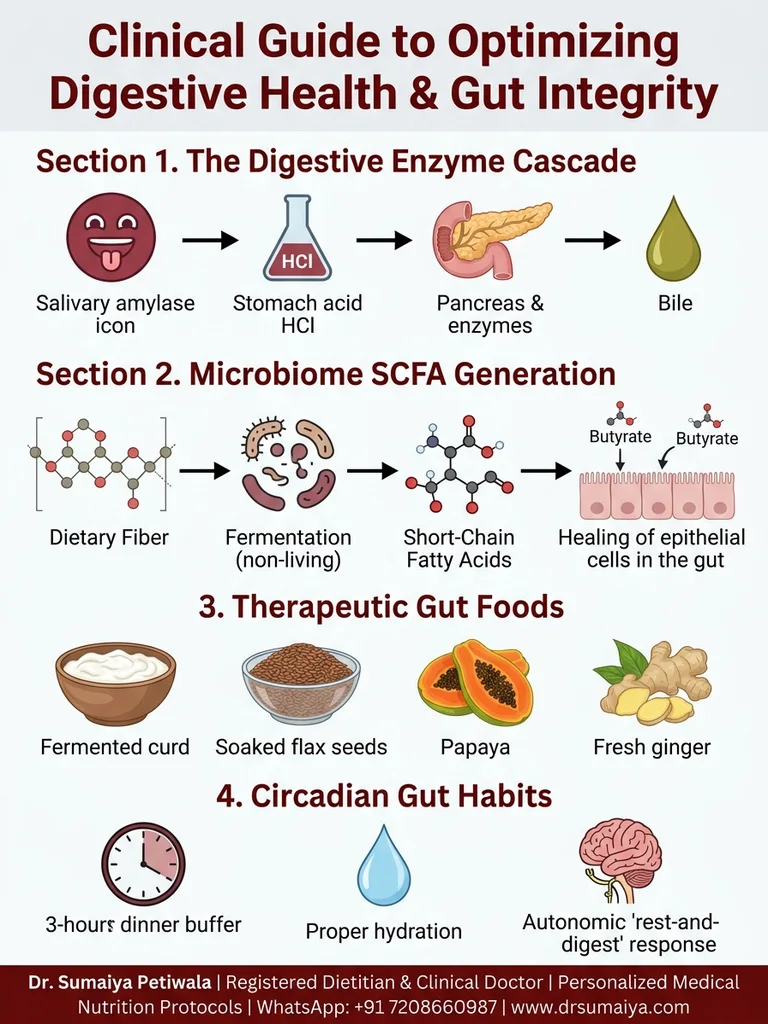
📊 Clinical Infographic: Digestive Physiology, Bowel Transit Biomechanics, and Doctor-Guided Gut Habits.
Stool Clues: What Your Bowel Movements Reveal About Digestive Health
A big drawback of modern Western toilets is that stools drop into deep water right away. Deep water dilutes color, hides mucus, and masks blood. An Indian squat toilet pan lets waste rest above the water trap. This gives you a clear view of daily health clues.
Doctors use the Bristol Stool Form Scale to check bowel transit speed. Looking at your stool once a day helps you catch early gut imbalances:
| Stool Appearance | Body Cause | Clinical Meaning | Dr. Sumaiya’s Nutrition Action |
|---|---|---|---|
| Hard, Dry Pellets (Type 1–2) | Slow gut transit; colon absorbs too much water | Constipation; low fiber and water | Add soaked isabgol and drink 2.5 liters of water daily |
| Smooth Soft Sausage (Type 3–4) | Balanced gut flora and ideal moisture | Normal transit speed | Keep your balanced Indian plate meals |
| Loose Mushy Stool (Type 5–6) | Fast transit or mild gut irritation | Food intolerance or mild dysbiosis | Eat curd rice with steamed lauki for two days |
| Black Tarry Stool (Melena) | Bleeding high in the stomach or upper gut | Gastric ulcer or upper gut bleeding | Red Flag: Visit an emergency hospital right away |
| Bright Red Blood | Fresh bleeding in the rectum or anus | Piles, fissures, or lower bowel polyp | See a doctor promptly; avoid all toilet pushing |
| Pale or Clay-Colored | Lack of bile pigment in the bowel | Bile duct stone or liver stress | See a doctor for liver blood tests and a scan |
| Greasy Floating Stools | Unabsorbed fats passing into the bowel | Fat malabsorption or pancreas fatigue | Cut heavy fried snacks; check gut enzymes |
| Persistent Mucus | Irritated intestinal lining making extra slime | Colitis, IBS, or gut inflammation | Focus on gut barrier repair and gentle healing foods |
Clinical Reality Check: Stool appearance gives useful clues, but it cannot replace blood or stool tests. Iron pills and beetroot can darken stool for a few days without harm. However, black tarry stools or unexplained rectal bleeding always require quick medical attention.
Urine Signals: Monitoring Hydration, Kidney Function and Health
Checking your urine gives fast clues about hydration and kidney health. In an Indian toilet, urine sits in the dry ceramic pan. In a Western commode, water dilutes urine right away. This dilution hides slight color shifts.
- Pale Straw or Light Yellow: Good hydration and smooth kidney filtration. Keep drinking your usual water.
- Dark Amber or Deep Honey: Concentrated urine from drinking too little water. Your kidneys are saving water to stop dehydration.
- Pink, Red, or Cola-Colored: May signal hematuria (the presence of red blood cells in your urine). Foods like beetroot can cause pink urine, but true blood needs quick medical checks.
- Cloudy or Murky Urine: Often points to a urinary infection or mineral crystals. You may also feel a burning sting when passing urine.
- Persistently Foamy Urine: May signal proteinuria (abnormal protein leakage in urine, an early indicator of kidney strain). Fast flow causes a few bubbles, but thick lasting foam needs a lab urine test.
Musculoskeletal Realities: When a Western Commode Is Medically Necessary
Squatting offers clear benefits for bowel emptying. Yet it is not safe for every person. Deep squatting forces knees and hips into extreme bends. For many adults, this posture brings real joint risks.
Use a Western commode under these medical conditions:
- Knee Osteoarthritis: In adults with osteoarthritis (age-related wear and tear of joint cartilage, causing knee stiffness and pain), deep squatting crushes worn cartilage. This can spark sharp knee pain and swelling.
- Hip Replacements and Surgery: Patients with a hip replacement must avoid bending hips past 90 degrees. Deep squats risk hip joint dislocation.
- Elderly Adults and Fall Risks: Stepping onto wet squat footplates causes slip-and-fall risks for seniors with balance trouble.
- Late-Stage Pregnancy: A growing belly shifts balance forward. Deep squatting becomes tiring and unsteady.
- Pelvic Organ Prolapse: Unsupported deep squatting can place heavy downward pressure on weak pelvic supports.
⚠️ Safety Warning: Musculoskeletal Boundaries
Never force a deep squat if your knees, hips, or back hurt. Passing stools should never injure your joints. If you have stiff joints, use a Western commode with a sturdy footstool.
The Practical Compromise: How to Use a Toilet Footstool with a Western Commode
You do not need to remodel your bathroom or hurt your knees to empty your bowels easily. A simple 7-inch to 9-inch toilet footstool turns a standard Western commode into an ergonomic semi-squat.
Follow this simple 5-step posture method:
- Sit Back Comfortably: Sit back on the commode seat. Keep your spine comfortably straight.
- Put Feet on the Stool: Place both feet flat on the footstool. Your knees should rise above your hip joints.
- Lean Your Upper Body Forward: Tilt your torso forward at about 35 degrees. Rest your elbows lightly on your knees.
- Relax Your Belly: Let your belly expand softly. Take slow belly breaths instead of holding your breath.
- Avoid Straining: Never push hard against a closed throat. Let natural bowel waves move waste along.
💡 Practical Clinical Tip: Leave Your Phone Outside
Leave your phone outside the bathroom. Sitting for long periods on a toilet seat pools blood in pelvic veins. Keep your bathroom visits under five minutes. If bowels do not move, stand up, drink warm water, and try again when the urge returns.
Why Toilet Posture Alone Cannot Cure Constipation: The Indian Kitchen Prescription
Fixing your toilet posture opens the exit pipe. Yet it cannot fix what is moving inside that pipe. If stool is rock-hard and dry, even the best squat cannot stop straining. Lasting gut health requires daily medical nutrition.
ICMR-NIN 2024 guidelines recommend about 30 grams of dietary fiber daily for adults. Most urban Indian meals give less than 15 grams, leading to chronic constipation (infrequent, dry, or difficult-to-pass bowel movements).
Use Dr. Sumaiya’s simple Indian kitchen habits for smooth daily bowel movements:
- The 50/25/25 Indian Plate Formula for Gut Motility:
- 50% of your plate: Cooked vegetable sabzi (lauki, tori, palak, methi, or bhindi) plus a fresh katori of salad (cucumber and carrot). These vegetables supply prebiotic (nourishing plant fibers that feed your beneficial gut bacteria) fuels.
- 25% of your plate: Clean plant protein, like thick yellow moong dal with jeera-hing tadka, boiled chana, or homemade paneer.
- 25% of your plate: Smart whole grains, like 1 or 2 phulkas of whole wheat atta or a measured katori of brown rice.
- Bedtime Soluble Fiber: Stir 1 teaspoon of pure isabgol (psyllium husk) into a glass of warm water before bed. Psyllium absorbs water and turns into a soft gel that eases hard stool pellets.
- Morning Hydration: Drink two glasses of lukewarm water with soaked methi seeds upon waking. Warm water wakes up your digestive reflex, telling your colon to contract.
- Daily Digestive Chaas: Drink a glass of fresh salted buttermilk after lunch with roasted jeera powder and mint. Fermented curd gives active probiotic (live, beneficial bacteria found in fermented foods like homemade curd) cultures to support your gut microbiome (the diverse community of beneficial bacteria living inside your digestive tract).
- The Meal Sequencing Hack: Eat your salad and sabzi first, your dal or paneer second, and your roti or rice last. This sequence coats your gut walls with fiber, blunting postprandial (after-meal) blood sugar surges while speeding transit.
Good metabolic health also protects your bowels. Insulin resistance (when your cells struggle to absorb blood sugar efficiently) and visceral fat (deep belly fat stored around your vital digestive organs) slow gut nerve signals. Tracking metabolic lab markers like fasting insulin (a morning blood test that measures your baseline insulin levels) and HbA1c (a standard blood test showing your average blood sugar over the past 3 months) keeps your gut and metabolism healthy together.
📌 Clinical Citation Unit Is an Indian toilet or Western commode healthier for digestion?
Squatting on an Indian toilet straightens the anorectal angle from 90 to 35 degrees by relaxing the puborectalis muscle, minimizing evacuation straining. For adults with knee osteoarthritis or balance concerns, a Western commode paired with a 7-inch footstool safely replicates these biomechanical benefits without stressing joint cartilage. Combining supported posture with 30 grams of daily Indian kitchen fiber ensures smooth colonic transit.
Frequently Asked Questions (FAQs)
References
- ICMR-NIN (2024). Dietary Guidelines for Indians: Recommended Dietary Allowances and Food-Based Dietary Guidelines. National Institute of Nutrition, Hyderabad. https://www.nin.res.in
- Sikirov, B. A. (2003). Comparison of straining during defecation in three positions: results and implications for human health. Digestive Diseases and Sciences, 48(7), 1201-1205. https://pubmed.ncbi.nlm.nih.gov/12870773/
- Sakakibara, R., et al. (2010). Influence of body position on defecation in humans. LUTS: Lower Urinary Tract Symptoms, 2(1), 16-21. https://pubmed.ncbi.nlm.nih.gov/26676061/
- Modi, R. M., et al. (2019). Implementation of a defecation postural modification device: impact on bowel movement characteristics in healthy subjects. Journal of Clinical Gastroenterology, 53(3), 216-219. https://pubmed.ncbi.nlm.nih.gov/30346317/
- Lewis, S. J., & Heaton, K. W. (1997). Stool form scale as a useful guide to intestinal transit time. Scandinavian Journal of Gastroenterology, 32(9), 920-924. https://pubmed.ncbi.nlm.nih.gov/9299672/
- American Gastroenterological Association (2023). Clinical Practice Guidelines on the Medical Management of Constipation. Gastroenterology, 164(6), 1086-1106. https://pubmed.ncbi.nlm.nih.gov/37024373/
This guide provides general health information. Your own care depends on your medical history and circumstances. Speak with your treating clinician before changing medicines or treatment.